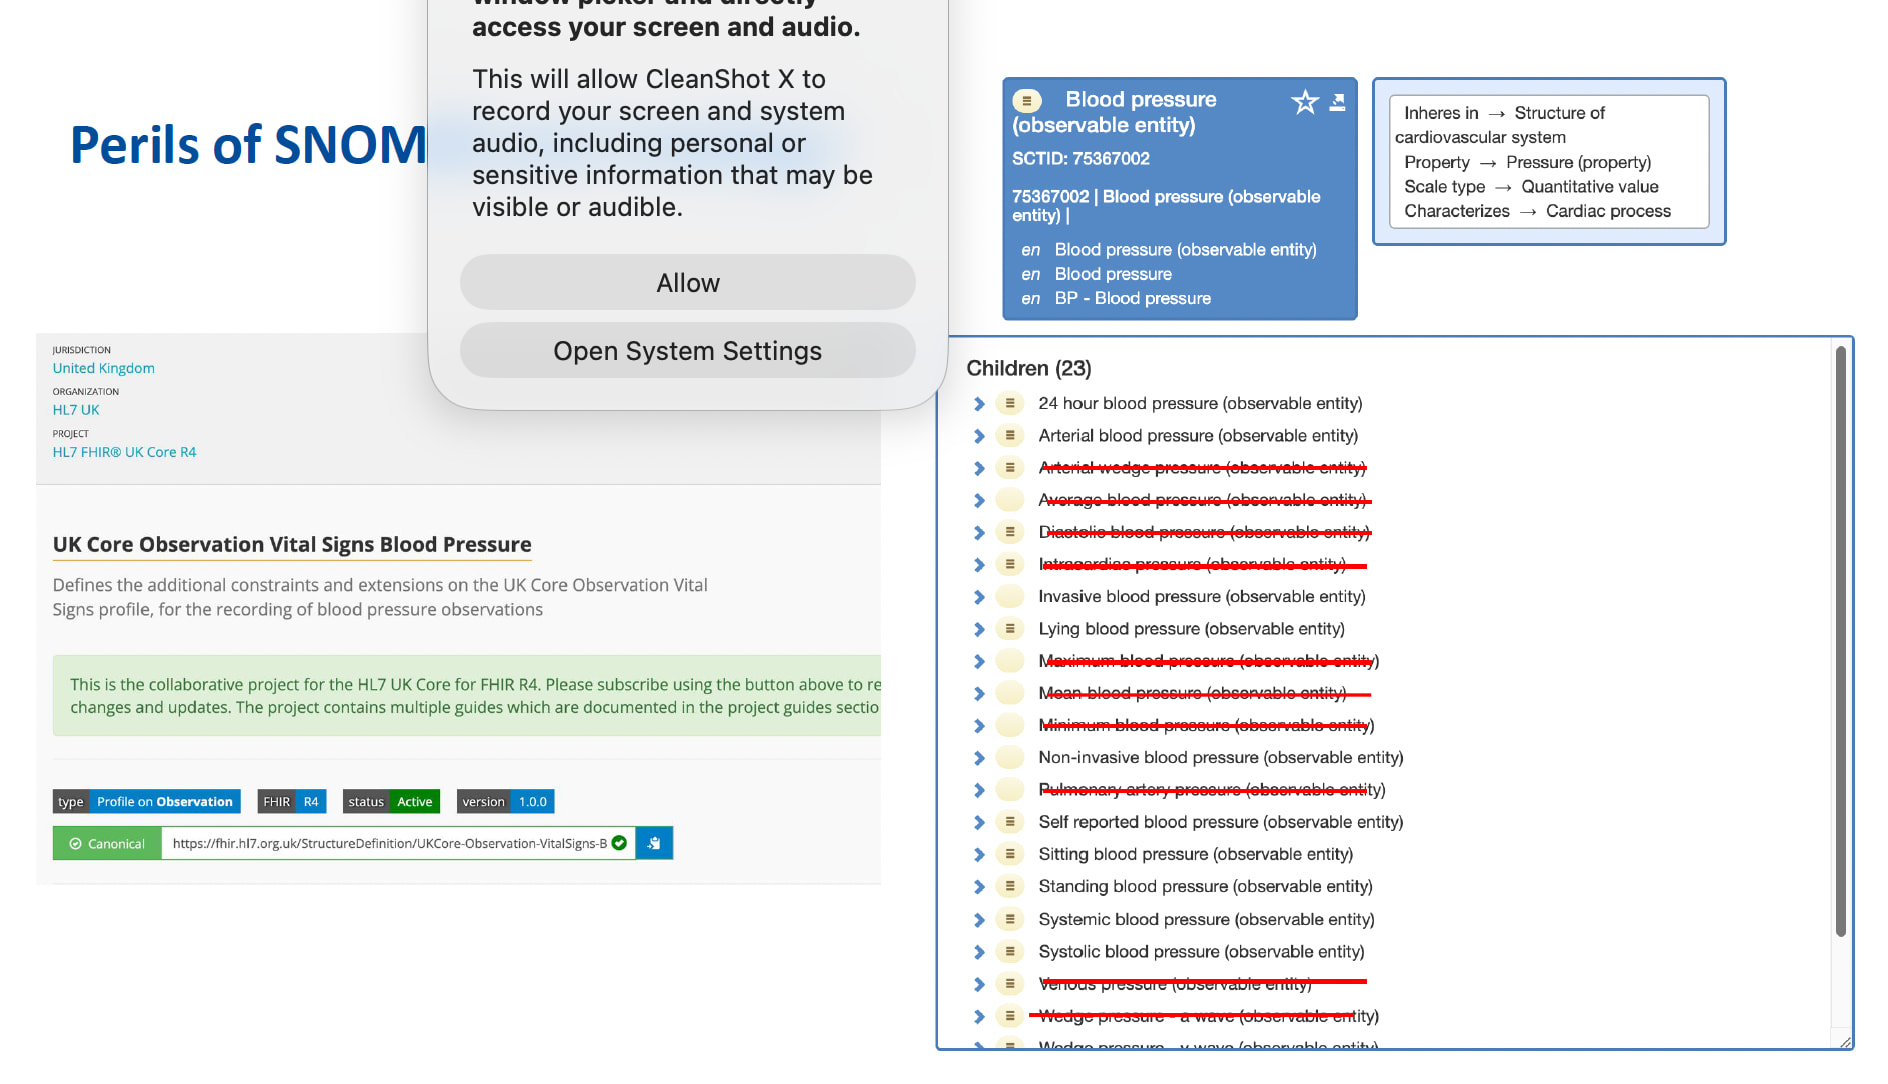
First of all, none of the terminology binding in international archetypes have gone through any form of formal review, so don’t rely on them being correct
However, I think this particular binding, which was added in revision 36 (1.1.3-alpha), probably is correct: The term 75367002 |Blood pressure (observable entity)| is quite generic, and encompasses both venous pressures and pulmonary pressures. The OBSERVATION.blood_pressure archetype on the other hand, is very specifically about systemic arterial pressure, which is what clinicians generally talk about when the term “blood pressure” is used without qualification.
Yes, completely agree with your reasoning. This actually came up in the UK when the SNOMED bondings for ‘blooad pressure’ turned out to be very misleading.
This was part of my assessment - the scored out items are types of pressures in parts of te vacular systems but they are not 'blood pressure in the normal clinical meaning , and which the archetype is explicitly designed to match.
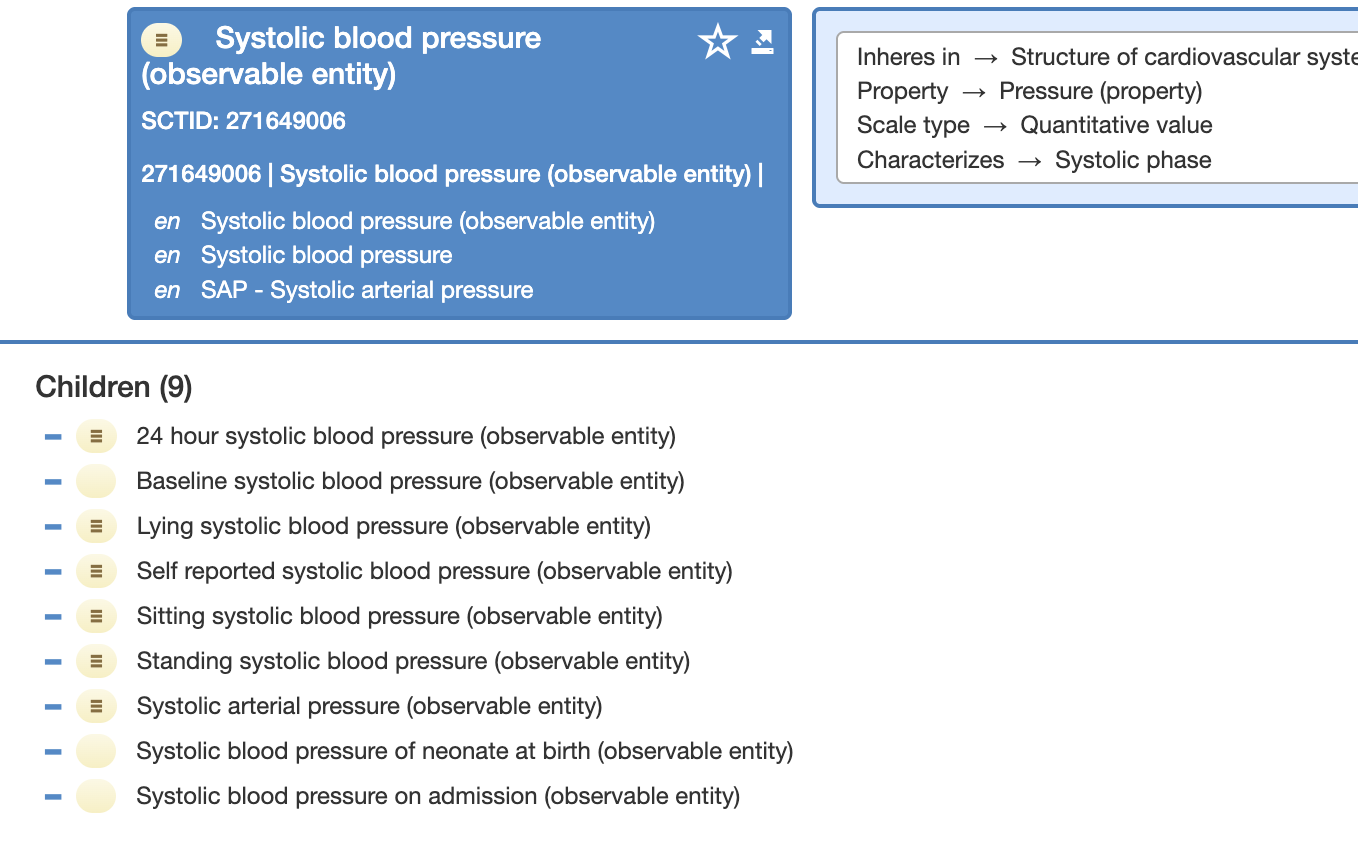
Although I agree that ‘Systemic Systolic arterial blood pressure’ is absolutely correct, I’m a bit more comfortable with ‘Systolic blood pressure’, if only because most of its descendants imply the correct concept.
I’d probably be happy to insert the correct Norwegian term as a synonym (preferred) for SAP - Systemic arterial pressure’.
Basically I think that part of the ontology is roughly correct but is just not linguistically precise. OTOH linking to 75367002 | Blood pressure (observable entity) | is just wrong (and the whole hierarchy is a mess).
Thanks for your valuable input. I do agree that the archetype is only about the arterial blood pressure but still needed more background to why the “generic” concept was not selected. I get your point. I was quite surprised that the Snomed link was there on Concept name level, I have missed it until last Tuesday even though I keep coming back to the archetype as I use it as an example in many contexts.
I also find the Snomed blood pressure concepts a bit of a jungle…
Wouldn’t the ideal SNOMED code be something along the lines of: “Recording of Arterial Blood Pressure Measurement” or “Result of Arterial Blood Pressure Measurement”?
Because we are only dealing with a bit of information about a measurement of the BP, not the actual, physical blood pressure, which is best left inside the patient…
@siljelb I would be hesitant about “systemic”, since at most we are using the result BP measurement result as a surrogate for the idea of a systemic BP, as laid out by the concept description in the Archetype.
That connection is based on the assumption that the vasculature between the aorta and our location of measurement is functioning normally.. which is OK to assume until it is not…
From my understading in aortic dissections etc it can be vital to recognize that the brachial artery BP may not be the same as the BP elsewhere…
And is there ever really one single systemic arterial blood pressure that anyone should be trying to put a single number on?
if there was no gradient across pressures in the large arteries, why would the blood flow?
I’ve come to suspect that at least part of the problems we’ve had trying to fit SNOMED CT concepts on to archetypes is caused by a difference between an ontology of physiological concepts (SNOMED CT) and an ontology of health record concepts (archetypes).
You’re right about the assumptions. The archetype does indirectly address this in the first misuse statement, but maybe it should be more explicit.
It is however important to be able to separate a BP measurement in on the systemic side from one on the pulmonary side. If we want to use a complex ontology like SNOMED CT to do that (which tbh I’m not 100% sure we do), we had better use terms that are sufficiently specific. Also when the shorter, everyday term used by clinicians is heaped high with implicit knowledge. Otherwise we could just as well have used a much simpler code list without all the complexity.
Plus I don’t think anyone ever wrote just ‘systolic BP’ to mean pulmonary circuit pressure, since the latter is a special catheter or echo measurement only done in a hospital AFAIK.
It certainly is. Full of precoordinated interface times mixed in with somewhat ontological entities. Uncomputable.
That’s the purpose of the Record Artifact hierarchy, but it is mainly intended for “container” concepts: reports, sections, etc.
Even if a concept such as “Recording of arterial blood pressure” existed, there would be the problem of deciding whether a particular archetype ENTRY is a record artifact or an observable entity. And this is not exclusive to SNOMED CT, LOINC suffers from a similar problem.
Snomed doesn’t know whether it is ontological (concept = Systemic arterial BP at systole) or epistemic (concept = measurement of …). it should be ontological, because the epistemic dimension is very context dependent. E.g. it could be a target BP for a hypertensive patient. Welcome to Snomed
@silje your comment is technically correct (and a lot of people don’t understand this ‘surrogate’ business), but it’s not up to the code or model to know if it is being used correctly in the clinic; we can only assume that if a systolic BP were recorded in the normal way on the arm that the person who did it was sufficiently competent to know that the patient was not in any state that would invalidate that measurement being the usual good-enough proxy for pressure in the systemic circuit. If someone has come in with aortic dissection we hope the docs know what they’re doing!